
Abstract
Keywords:
Diabetic foot, osteomyelitis, antimicrobial resistanceIntroduction
With the increasing prevalence of diabetes, diabetic foot ulcers are being encountered more frequently. It has been reported that infection develops in more than half of patients with diabetes-related foot ulcers, and that amputation is required in approximately 20% of moderate to severe cases (1). Diabetic foot infections most commonly arise in the setting of these ulcers and encompass a broad clinical spectrum, ranging from superficial soft tissue infections to deep tissue infections, osteomyelitis, and necrotizing infections. Due to the wide clinical spectrum, accurate patient assessment and determination of infection severity are critical for planning appropriate treatment strategies. Bone involvement during diabetes-related foot infection is a serious complication associated with an increased risk of amputation, prolonged antibiotic therapy, and hospitalization. Current clinical guidelines recommend systematic classification of infection severity to provide a standardized approach to the management of diabetic foot infections (2–4).
Diabetes-related foot infections are often polymicrobial, and the duration of treatment varies depending on patient-specific factors (5). Complications such as osteomyelitis frequently require prolonged and broad-spectrum antibiotic therapy; however, this approach may contribute to the development of antimicrobial resistance. In addition, patient-specific risk factors may influence the diversity of microbiological pathogens, which limits the suitability of a single empirical treatment approach for all cases (6).
Studies evaluating the relationship between the presence of osteomyelitis and clinical findings, classification systems, and microbiological characteristics in combination are limited in the literature. In particular, the literature needs to better characterize the clinical and microbiological features associated with osteomyelitis. Therefore, in this study, clinical characteristics, risk factors, antimicrobial resistance profiles, and Site, Ischemia, Neuropathy, Bacterial infection, Area, and Depth (SINBAD) and Wound, Ischemia, and foot Infection (WIfI) classification parameters were compared according to the presence of osteomyelitis in patients with diabetes-related foot infection.
Materials and Methods
Study Design and Patient Selection
This retrospective study included patients who presented to the outpatient clinic or were hospitalized with a diagnosis of diabetes-related foot infection at a secondary-care hospital between April 15, 2025, and April 15, 2026. Patients with clinically diagnosed diabetes and an infected foot lesion from whom at least one microbiological sample was obtained during the evaluation process were included in the study. Patients were divided into two groups according to the presence of concomitant osteomyelitis: those with diabetes-related foot infection with osteomyelitis and those without concomitant osteomyelitis. Thereafter, these groups were referred to as the osteomyelitis and non-osteomyelitis groups, respectively. The groups were compared in terms of demographic characteristics, clinical risk factors, wound classification parameters, laboratory findings, microbiological pathogen distribution, and antimicrobial resistance profiles.
The unit of analysis for demographic, clinical, laboratory, and classification variables was the individual patient.
In cases where the same patient had multiple hospitalizations or infection episodes, each episode was considered an independent infection, provided that clinical recovery had been achieved after the previous infection and at least 30 days had elapsed, or that a new focus of infection had developed. Previous antibiotic exposure was defined as systemic antibiotic use within one month before admission for the current diabetes-related foot infection episode. Demographic and clinical data were obtained from electronic medical records.
The study was approved by the Non-Interventional Clinical Research Ethics Committee of Aydın Adnan Menderes University Faculty of Medicine on June 18, 2026, with decision no. 2026/240.
Inclusion Criteria
Age ≥18 years.
Admission to our hospital with a diagnosis of diabetes-related foot infection between April 15, 2025, and April 15, 2026.
Having been diagnosed with a diabetic foot infection according to the International Working Group on the Diabetic Foot (IWGDF) criteria and having had the severity of infection graded.
Diagnosis of osteomyelitis established in accordance with IWGDF recommendations based on clinical findings, imaging methods (plain radiography or magnetic resonance imaging), and, when necessary, surgical findings or histopathological evaluation results.
Availability of an aspiration, deep tissue, or bone sample obtained from the wound for microbiological examination.
Availability of sufficient clinical and laboratory data for analysis in electronic medical records.
Exclusion Criteria
Age <18 years
Absence of an aspiration, deep tissue, or bone sample obtained from the wound site
Microorganism isolates considered contaminants or not clinically significant
Repeated culture samples from the same infection episode
Patients with missing or incorrect clinical or laboratory data
Patients presenting with infections or foot lesions other than diabetes-related foot infection
Individuals experiencing homelessness
Patients with immunodeficiency
Patients diagnosed with vasculitis
Diagnosis of Osteomyelitis and Wound Classification
In patients with diabetic foot infection, wound and infection classifications were used to evaluate the clinical characteristics and severity of the lesion, as recommended by the International Working Group on the Diabetic Foot/Infectious Diseases Society of America (IWGDF/IDSA) guidelines. Osteomyelitis was diagnosed in accordance with the same guidelines through the combined evaluation of clinical, laboratory, and radiological findings (4,7). Scores were calculated based on the clinical assessment at the time of initial admission.
Surgical Sampling Procedure
Microbiological samples were obtained intraoperatively or at the bedside, depending on the patient's clinical status. Under sterile conditions, any necrotic tissue present in the wound area was debrided using appropriate surgical techniques. Following debridement, deep tissue, aspirate, or bone specimens were collected from the clinically infected area using sterile instruments. Superficial swab cultures were excluded from the analysis. The specimens were transported to the microbiology laboratory under sterile conditions for further analysis.
Microbiological Analysis
From the prepared fluid suspension of the specimen, 0.05 mL was inoculated onto 5% sheep blood agar and MacConkey agar plates using a sterile loop under aseptic conditions. The inoculated plates were incubated aerobically at 35°C and examined for microbial growth after 24 hours. If no growth was observed, the plates were re-incubated and reassessed at 48 hours post-inoculation.
Bacterial identification was performed using conventional biochemical methods. Upon detection of microbial growth, isolates were initially evaluated by Gram staining. Gram-negative organisms were identified based on standard biochemical characteristics, including glucose, sucrose, and lactose fermentation; citrate utilization; motility; urease and indole production; ornithine decarboxylase activity; and oxidase reaction. Gram-positive organisms were identified according to catalase activity, hemolytic patterns, coagulase production, susceptibility to optochin, bacitracin, and trimethoprim-sulfamethoxazole, as well as growth on bile esculin agar and in media containing 6.5% sodium chloride. Anaerobic cultures could not be performed.
Microbiological pathogen distribution and antimicrobial resistance profiles were evaluated on an isolate basis. Because more than one microorganism could be isolated from patients with polymicrobial growth, the number of isolates exceeded the number of patients.
Antibiotic Susceptibility Testing
Bacterial identification was performed using conventional biochemical methods. Antimicrobial susceptibility testing was performed and interpreted according to European Committee on Antimicrobial Susceptibility Testing (EUCAST) guidelines. Methicillin-resistant Staphylococcus aureus (MRSA) was identified using the cefoxitin disk diffusion method in accordance with EUCAST criteria. Ampicillin-resistant enterococci were identified according to EUCAST breakpoints (8).
Extended-spectrum beta-lactamase (ESBL)-producing isolates were defined, in accordance with EUCAST recommendations, as isolates showing reduced susceptibility to third-generation cephalosporins and, when necessary, confirmed phenotypically. The presence of inducible beta-lactamase (IBL), including AmpC beta-lactamase, was evaluated according to EUCAST expert rules and susceptibility patterns (8).
Multidrug-resistant (MDR) microorganisms were defined as isolates resistant to at least three different antimicrobial classes, in accordance with the criteria recommended by the European Centre for Disease Prevention and Control (ECDC) and the Centers for Disease Control and Prevention (CDC) (9,10).
Statistical Analysis
The assumption of normal distribution for quantitative variables was assessed using the Kolmogorov-Smirnov test. Descriptive statistics were presented as mean ± standard deviation for normally distributed quantitative variables, median (25th–75th percentile) for non-normally distributed variables, and frequency (%) for categorical variables. For independent group comparisons, the independent samples t-test was used for normally distributed variables, and the Mann-Whitney U test was used for non-normally distributed variables. Associations between categorical variables were evaluated using the chi-square test. A p value of < 0.05 was considered statistically significant.
Results

Osteomyelitis was detected in 49 of the 95 patients included in the study, while 46 patients had no evidence of osteomyelitis. Patients were divided into two groups according to the presence of osteomyelitis and analyzed accordingly.
When categorical variables were examined, the rate of recurrent foot infection in the osteomyelitis group (77.6%) was significantly higher than that in the non-osteomyelitis group (52.2%) (p = 0.009). The proportion of patients with a previous history of osteomyelitis was significantly higher in the osteomyelitis group (53.1%) than in the non-osteomyelitis group (13.0%) (p < 0.001). In addition, the rate of previous peripheral vascular intervention was significantly higher in the osteomyelitis group (69.4%) than in the non-osteomyelitis group (28.3%) (p < 0.001). The rate of antibiotic use within the previous month was also significantly higher in the osteomyelitis group (91.8%) than in the non-osteomyelitis group (76.1%) (p = 0.035). Detailed data for all variables are presented in Table 1.
The neuropathy rate was significantly higher in the osteomyelitis group (85.7%) than in the non-osteomyelitis group (61.4%) (p = 0.07). The rate of antimicrobial resistance was also significantly higher in the osteomyelitis group (59.2%) than in the non-osteomyelitis group (34.8%) (p = 0.017). When laboratory findings were evaluated, both C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR) levels were significantly higher in the osteomyelitis group than in the non-osteomyelitis group (p = 0.007 and p = 0.003, respectively). Detailed data are presented in Table 2.

Patients with positive cultures were additionally analyzed by dividing them into two groups according to antimicrobial resistance status. The mean age was significantly lower in the group with antimicrobial resistance (60.76 ± 10.23) than in the group without antimicrobial resistance (67.36 ± 9.87) (p = 0.002).
When categorical variables were evaluated, the rate of a previous history of osteomyelitis was significantly higher in the group with antimicrobial resistance (44.4%) than in the group without antimicrobial resistance (24.0%) (p = 0.035). No statistically significant differences were found between the groups with respect to other clinical characteristics (p > 0.05). Detailed data are presented in Table 3.

As shown in Table 4, the infection classification score was significantly higher in the group with antimicrobial resistance than in the group without antimicrobial resistance (p = 0.003). When laboratory findings were evaluated, CRP levels were significantly higher (p = 0.018), whereas hemoglobin (Hb) levels were significantly lower in the group with antimicrobial resistance (p = 0.028).
In the microbiological evaluation, microbial growth was detected in all patients in the osteomyelitis group, whereas no growth was observed in 15 of the 46 patients in the non-osteomyelitis group. Among patients with positive cultures, polymicrobial growth was more frequent in the osteomyelitis group (34.7%) than in the non-osteomyelitis group (16.1%).
The isolate-based microorganism distribution and antimicrobial resistance rates according to the presence of osteomyelitis are presented in Table 5. In the isolate-based evaluation, Gram-negative bacteria accounted for 56.8% of isolates and Gram-positive bacteria for 43.2% in the non-osteomyelitis group. The most frequently isolated pathogens in this group were S. aureus (18.9%), Klebsiella pneumoniae (13.5%), and Pseudomonas aeruginosa (13.5%). In the osteomyelitis group, Gram-negative bacteria accounted for 56.7% of isolates and Gram-positive bacteria for 43.3%. The most frequently isolated pathogens in this group were S. aureus (22.4%), Escherichia coli (11.9%), and P. aeruginosa (10.4%). No statistically significant difference was found between the groups in terms of the overall distribution of Gram-positive and Gram-negative bacteria. Among the individual microorganisms, only Acinetobacter spp. was significantly more frequent in the non-osteomyelitis group than in the osteomyelitis group (p = 0.043). No statistically significant differences were detected between the groups for the other microorganisms or antimicrobial resistance patterns.

When resistance profiles were evaluated, the MDR rate among Gram-negative isolates was 33.3% in the non-osteomyelitis group and 44.7% in the osteomyelitis group. Extended-spectrum beta-lactamase production was observed only in the non-osteomyelitis group (9.5%), whereas IBL production was detected only in the osteomyelitis group (5.3%). Among Gram-positive pathogens, the MRSA rate among S. aureus isolates was numerically higher in the osteomyelitis group than in the non-osteomyelitis group (66.7% vs. 42.9%). Similarly, methicillin resistance among coagulase-negative staphylococcal isolates was numerically higher in the osteomyelitis group than in the non-osteomyelitis group (75.0% vs. 50.0%). Among Enterococcus spp. isolates, ampicillin resistance was detected only in the non-osteomyelitis group (25.0%). However, these differences in antimicrobial resistance patterns were not statistically significant.
Discussion
In this study, the relationship between the presence of osteomyelitis and clinical characteristics, as well as microbiological resistance profiles, and clinical classification scores was evaluated in patients with diabetes-related foot infections. Our findings showed that osteomyelitis was associated with recurrent foot infection, a history of previous osteomyelitis, previous peripheral vascular intervention, neuropathy, and antibiotic use within the previous month.

In our study, a history of peripheral vascular intervention was more frequent in the osteomyelitis group. In diabetes-related foot infection with osteomyelitis, inadequate local circulation due to peripheral vascular disorders may hinder the achievement of sufficient antibiotic concentrations at the site of infection, thereby making the control of infection more difficult (11). This condition may contribute to the chronicity of infection and predispose patients to the development of osteomyelitis through recurrent infections. In addition, neuropathy was more frequent in the osteomyelitis group. Diabetic neuropathy facilitates the development of recurrent trauma and ulceration by causing the loss of protective sensation, and this process predisposes patients to the development of osteomyelitis through the spread of infection to deeper tissues (12). This finding suggests that neuropathy may play an important role not only in the development of ulcers but also in the progression of infection to bone involvement.
The literature indicates that inflammatory markers such as CRP have limited sensitivity and specificity for the diagnosis of osteomyelitis and that these markers are more useful in distinguishing infectious from non-infectious foot pathologies (13). In our study, both CRP and ESR levels were significantly higher in patients with osteomyelitis than in those without osteomyelitis. This finding suggests that patients with bone involvement had a greater systemic inflammatory burden. In the literature, ESR has been reported to be more closely associated with diabetic foot osteomyelitis than CRP (14). However, inflammatory markers alone are insufficient to establish the diagnosis of osteomyelitis, and current recommendations emphasize their interpretation alongside clinical findings, probe-to-bone test results, imaging, and microbiological or histopathological evidence, when available (4). Therefore, the elevated ESR and CRP levels observed in our study should be interpreted as supportive group-level findings rather than independent diagnostic markers for osteomyelitis.
In the microbiological evaluation, polymicrobial growth was more frequent in the osteomyelitis group than in the non-osteomyelitis group. This finding is consistent with studies reporting that infection in diabetes-related foot infections with concomitant osteomyelitis may be associated with complex microbial communities rather than a single pathogen. A study in which bone samples from cases of diabetes-related foot infection with osteomyelitis were examined using molecular and microscopic methods demonstrated that polymicrobial communities and biofilm structures can frequently be observed in these cases. Therefore, the more frequent detection of polymicrobial growth in the osteomyelitis group in our study may reflect the deeper, more chronic, and more complicated nature of bone infection (15).
The finding that S. aureus was the most frequently isolated pathogen in both groups is consistent with the literature reporting this microorganism as one of the principal pathogens in diabetes-related foot infections and with recent multicenter data on diabetic foot osteomyelitis (16). While the MRSA rate among S. aureus isolates was reported as 20.8% in that study, the higher MRSA rate observed in the osteomyelitis group in our study may be related to center-specific resistance characteristics and antibiotic use within the previous month. One study reported that, in addition to S. aureus being frequently isolated in diabetic foot infections, it can persist in the chronic wound environment and may undergo genomic changes over time (17). This finding supports the view that, particularly in chronic and complicated cases, S. aureus is not only a common pathogen but also an important microorganism in terms of patient follow-up and treatment.
One of the notable findings of this study was that both antimicrobial resistance and antibiotic use within the previous month were significantly higher in the osteomyelitis group. The literature indicates that previous antibiotic use and the presence of osteomyelitis may be associated with multidrug-resistant microorganisms; in addition, discordance between soft tissue and bone cultures in diabetes-related foot infections with concomitant osteomyelitis has been reported to contribute to the development of resistance by increasing the use of broad-spectrum antibiotics (18,19). In a prospective multicenter study conducted in Türkiye, resistant bacterial growth was detected in 43% of diabetes-related foot infection cases; antibiotic use within the previous 30 days was identified as an independent risk factor for resistant bacterial growth, and resistant bacterial growth was found to be associated with treatment failure and increased antibiotic costs (20). Similarly, another study from Türkiye reported an MDR rate of 47.9% in diabetes-related foot infection and demonstrated that MDR growth was associated with polymicrobial growth and a history of hospitalization (21). Recent cohort data have also emphasized that antimicrobial-resistant pathogens complicate the management of diabetes-related foot infection and may be associated with poor clinical outcomes (22). These findings support the possibility that the high resistance rates observed in the osteomyelitis group in our study may be related to previous antibiotic exposure, the polymicrobial nature of the infection, and complicated clinical characteristics. Although the higher rate of resistant microorganism isolation in the younger age group was a notable finding in our study, this observation does not fully align with the classical risk factors described in the literature. A meta-analysis found no significant association between age and multidrug-resistant organism (MDRO) infection; however, previous hospitalization, antibiotic use, osteomyelitis, ulcer size, vascular disease, and a history of surgical intervention were identified as more consistent risk factors (23). Therefore, the high resistance rates observed in younger patients and the elevated prevalence of MDROs in our study are consistent with the literature when considered in the context of recent antibiotic use and healthcare exposure rather than as a direct effect of age.
Although bone biopsy (histology and culture) is considered the gold standard for the diagnosis of osteomyelitis, the diagnostic process generally begins with clinical evaluation. Accurate identification of the causative microorganism is critical for treatment. However, studies evaluating the diagnostic value of clinical and laboratory findings remain limited (24).
In the evaluation of clinical classification systems, no significant association was found between osteomyelitis and either the SINBAD score or the IWGDF wound classification. Although the literature has shown that the SINBAD score is associated with adverse clinical outcomes such as amputation, hospitalization, and secondary infection, its role in predicting deep infections such as osteomyelitis remains unclear (25). In contrast, the WIfI classification was developed primarily to predict limb prognosis because it simultaneously evaluates wound, ischemia, and infection components, and therefore has the potential to reflect outcomes related to the depth of infection (4). However, studies directly evaluating the performance of these classification systems in predicting the presence of osteomyelitis remain limited in the current literature.
Our study has several limitations. First, anaerobic cultures could not be performed. Therefore, we were unable to determine the role of anaerobic microorganisms in diabetes-related foot infections. In addition, the limited number of patients and the small number of isolates in some subgroups made the interpretation of subgroup analyses, particularly those involving MRSA, ESBL, AmpC/IBL, and enterococcal resistance, more challenging. Because the microbiological analyses presented in Table 5 were performed on an isolate basis, multiple isolates obtained from the same patient or infection episode could be included in the analysis. Therefore, these observations may not have been statistically independent, and within-patient or within-episode clustering may have affected the variance estimates and p values. Accordingly, the statistical comparisons presented in Table 5 should be interpreted with caution. Another limitation is that comorbidities were evaluated as an overall variable rather than being analyzed separately according to individual conditions or secondary infection foci.
Nevertheless, our study also has several strengths. These include the comparison of diabetes-related foot infections with and without osteomyelitis not only in terms of clinical characteristics but also with respect to microbiological pathogen distribution, antimicrobial resistance profiles, laboratory findings, and classification systems. Furthermore, the separate analysis of patients according to the presence of resistant microorganism growth contributed to the identification of clinical characteristics associated with antimicrobial resistance. The use of real-world data and the reflection of secondary care hospital practice enhance the relevance of our findings for everyday clinical practice.
In conclusion, in patients with diabetes-related foot infection, concomitant osteomyelitis was associated with recurrent foot infection, a history of previous osteomyelitis, previous peripheral vascular intervention, neuropathy, antibiotic use within the previous month, elevated CRP and ESR levels, and resistant microorganism growth. Microbiologically, S. aureus was the most frequently isolated pathogen, while polymicrobial growth, the rate of Gram-negative MDR organisms, and the MRSA rate appeared to be higher in the osteomyelitis group. These findings support the need for individualized empirical treatment decisions in diabetes-related foot infections with concomitant osteomyelitis, taking into account the patient's previous antibiotic use, healthcare exposure, risk of antimicrobial resistance, and local microbiological data.
REFERENCES
Wang Q, Liu C, An J, Liu J, Wang Y, Cai Y. Mechanisms of microbial infection and wound healing in diabetic foot ulcer: pathogenicity in the inflammatory-proliferative phase, chronicity, and treatment strategies. Front Endocrinol. 2025 Oct 1;16:1657928. [CrossRef]
Senneville É, Lipsky BA, Abbas ZG, Aragón-Sánchez J, Diggle M, Embil JM, et al. Diagnosis of infection in the foot in diabetes: a systematic review. Diabetes Metab Res Rev. 2020;36(Suppl. 1):e3281. [CrossRef]
Giurato L, Meloni M, Izzo V, Uccioli L. Osteomyelitis in diabetic foot: A comprehensive overview. World J Diabetes. 2017 Apr 15;8(4):135–42. [CrossRef]
Senneville É, Albalawi Z, van Asten SA, Abbas ZG, Allison G, Aragón-Sánchez J, et al. IWGDF/IDSA guidelines on the diagnosis and treatment of diabetes-related foot infections (IWGDF/IDSA 2023). Diabetes Metab Res Rev. 2024;40(3):e3687. [CrossRef]
Ertuğrul B, Uçkay I, Schöni M, Peter-Riesch B, Lipsky BA. Management of diabetic foot infections in the light of recent literature and new international guidelines. Expert Rev Anti Infect Ther. 2020;18(4):293–304. [CrossRef]
Hawkins BK, Barnard M, Barber KE, Stover KR, Cretella DA, Wingler MJB, et al. Diabetic foot infections: A microbiologic review. Foot. 2022 May;51:101877. [CrossRef]
Monteiro-Soares M, Hamilton EJ, Russell DA, Srisawasdi G, Boyko EJ, Mills JL, et al. Guidelines on the classification of foot ulcers in people with diabetes (IWGDF 2023 update). Diabetes Metab Res Rev. 2024 Mar;40(3):e3648. [CrossRef]
European Committee on Antimicrobial Susceptibility Testing. Clinical Breakpoint Tables v. 16.0 [Internet]. EUCAST; 2026 [cited May 27, 2026]. Available from: https://www.eucast.org/bacteria/clinical-breakpoints-and-interpretation/clinical-breakpoint-tables/
CDC. Infection Control [Internet]. 2024 [cited May 27, 2026]. Background. Available from: https://www.cdc.gov/infection-control/hcp/mdro-management/background.html
Magiorakos AP, Srinivasan A, Carey RB, Carmeli Y, Falagas ME, Giske CG, et al. Multidrug-resistant, extensively drug-resistant and pandrug-resistant bacteria: an international expert proposal for interim standard definitions for acquired resistance. Clin Microbiol Infect. 2012;18(3):268–81. [CrossRef]
Yin SJ, Li J, Ren Y, Yang H, Li YX, Zhang H. Diabetic foot osteomyelitis: pathological microenvironment and matching tailored treatment strategies. Front Cell Dev Biol. 2026;14:1794273. [CrossRef]
Venkatesan V, Rangasamy J. Diabetic Pedal Osteomyelitis and Its Treatment. Chonnam Med J. 2023 May;59(2):109–14. [CrossRef]
Ertuğrul MB. Diyabetik Ayak Enfeksiyonunda Osteomiyelit Tanısı. Türkiye Klin Ortop Travmatoloji - Özel Konular [Internet]. 2020 [cited May 23, 2026];13(1):84–8. Available from: https://www.turkiyeklinikleri.com/article/tr-diyabetik-ayak-enfeksiyonunda-osteomiyelit-tanisi-87807.html
Ansert EA, Tarricone AN, Coye TL, Crisologo PA, Truong D, Suludere MA, et al. Update of biomarkers to diagnose diabetic foot osteomyelitis: A meta-analysis and systematic review. Wound Repair Regen. 2024;32(4):366–76. [CrossRef]
Johani K, Fritz BG, Bjarnsholt T, Lipsky BA, Jensen SO, Yang M, et al. Understanding the microbiome of diabetic foot osteomyelitis: insights from molecular and microscopic approaches. Clin Microbiol Infect. 2019 Mar 1;25(3):332–9. [CrossRef]
Soldevila-Boixader L, Murillo O, Waibel FWA, Schöni M, Aragón-Sánchez J, Gariani K, et al. The increasing prevalence of Enterobacteriaceae as pathogens of diabetic foot osteomyelitis: A multicentre European cohort over two decades. Int J Infect Dis. 2025 May;154:107843. [CrossRef]
Lavigne JP, Hosny M, Dunyach-Remy C, Boutet-Dubois A, Schuldiner S, Cellier N, et al. Long-Term Intrahost Evolution of Staphylococcus aureus Among Diabetic Patients With Foot Infections. Front Microbiol. 2021 Sep 6;12:741406. [CrossRef]
Guo H, Song Q, Mei S, Xue Z, Li J, Ning T. Distribution of multidrug-resistant bacterial infections in diabetic foot ulcers and risk factors for drug resistance: a retrospective analysis. PeerJ. 2023 Oct 9;11:e16162. [CrossRef]
Ertugrul MB, Baktiroglu S, Salman S, Unal S, Aksoy M, Berberoglu K, et al. Pathogens Isolated From Deep Soft Tissue and Bone in Patients With Diabetic Foot Infections. J Am Podiatr Med Assoc. 2008 Jul;98(4):290–5. [CrossRef]
Ertugrul BM, Oncul O, Tulek N, Willke A, Sacar S, Tunccan OG, et al. A prospective, multicenter study: factors related to the management of diabetic foot infections. Eur J Clin Microbiol Infect Dis. 2012;31(9):2345–53. [CrossRef]
Utlu Y, Başak O, Bozkurt-Kozan F, Ertuğrul MB. Causative agents and factors associated with multidrug-resistant pathogens in diabetic foot infections. Klimik Derg. 2019;32(1):84–9. Turkish. [CrossRef]
Zambelli R, Santos AF, Moreira LR, Ribeiro HM, Simões R, Magalhães JM, et al. Bacterial profile and antimicrobial resistance in diabetic foot ulcer infections: a 10-year retrospective cohort study. Braz J Infect Dis. 2025 Sep 1;29(5):104570. [CrossRef]
Xia W, He W, Luo T, Tang N. Risk factors for multidrug-resistant bacterial infections in patients with diabetic foot ulcers: a systematic review and meta-analysis. Ann Palliat Med. 2021 Dec;10(12):12618–30. [CrossRef]
Ertugrul BM, Savk O, Ozturk B, Cobanoglu M, Oncu S, Sakarya S. The diagnosis of diabetic foot osteomyelitis: examination findings and laboratory values. Med Sci Monit. 2009;15(6):CR307–12. [CrossRef]
Ha Van G, Schuldiner S, Sultan A, Bouillet B, Martini J, Vouillarmet J, et al. Use of the SINBAD score as a predicting tool for major adverse foot events in patients with diabetic foot ulcer: A French multicentre study. Diabetes Metab Res Rev. 2023;39(8):e3705. [CrossRef]
Abstract
Keywords:
Diabetic foot, albumin, PEDIS, nutritional status, wound infection, prognosisIntroduction
Diabetic foot ulcers represent a complex clinical condition influenced by the combined effects of neuropathy, ischemia, infection, impaired glycemic control, and the patient's systemic reserve (1). In these patients, wound healing is closely associated not only with local wound care and surgical interventions but also with infection control, metabolic regulation, and adequate nutritional support. Particularly in infected diabetic foot wounds, the increased inflammatory response and catabolic state increase the protein and energy requirements necessary for tissue repair, thereby affecting clinical outcomes, length of hospital stay, and treatment response.
Although numerous adjunctive treatment modalities—including regenerative products, skin grafts, negative pressure wound therapy, and hyperbaric oxygen therapy—are currently used to shorten treatment duration in diabetic foot management, the success of these approaches is largely influenced by the patient's systemic condition and nutritional reserve (2–4). Nutritional status is one of the key determinants of wound healing in diabetic foot disease. Adequate protein and energy intake are essential for collagen synthesis, granulation tissue formation, angiogenesis, immune regulation, and epithelialization (5,6). Therefore, assessment of nutritional reserve in patients with diabetic foot disease is important not only for planning supportive treatment but also for providing prognostic information regarding infection severity and the clinical course. In general surgical practice, this assessment is often based on practical, readily available, and reproducible laboratory parameters.
Serum albumin is one of the most commonly used biochemical markers for evaluating nutritional reserve in clinical practice. However, albumin levels reflect not only nutritional status but also systemic inflammatory activity and are influenced by several factors, including the inflammatory response, catabolic state, fluid balance, and hepatic synthetic capacity. Consequently, low serum albumin levels should be considered not only an indicator of malnutrition but also a marker of ongoing inflammatory and catabolic processes (7,8). In this respect, albumin may provide practical information regarding both nutritional status and the systemic impact of the disease in patients with diabetic foot infection.
Previous studies have suggested that low serum albumin levels in patients with diabetic foot disease may be associated with delayed wound healing, increased infectious burden, prolonged hospitalization, and unfavorable clinical outcomes (9). However, this relationship may not be uniform across all patient populations and should be interpreted in conjunction with disease severity. Unlike C-reactive protein (CRP) and white blood cell (WBC) count, serum albumin may provide additional clinical information by reflecting both nutritional reserve and inflammation-related systemic burden in patients with diabetic foot infection. The PEDIS classification is widely used to assess diabetic foot ulcers based on key clinical components, including perfusion, extent, depth, infection, and sensory loss (10). Therefore, evaluating serum albumin levels together with PEDIS Infection Grade, length of hospital stay, duration of intravenous antibiotic therapy, and duration of enteral nutritional support may contribute to the clinical management of patients with diabetic foot infection.
Nevertheless, studies investigating the relationship between serum albumin levels and PEDIS Infection Grade, as well as treatment-related clinical parameters in patients with diabetic foot infection, remain limited. The present study aimed to evaluate the association between admission serum albumin levels, infection severity, and clinical outcomes in patients hospitalized for diabetic foot infection.
Materials and Methods
Study Design and Patient Selection
This single-center observational cohort study was designed as a retrospective analysis of patients hospitalized for diabetic foot wounds and treated surgically (debridement or amputation) in the Department of General Surgery at Gülhane Training and Research Hospital between January and April 2025.
Among patients hospitalized for diabetic foot wounds and managed surgically in our clinic, those with inadequate oral intake requiring enteral nutritional support were included in the study.
Adult patients hospitalized and treated for diabetic foot disease were eligible for inclusion. Patients with incomplete clinical or laboratory data were excluded. Patients who did not undergo surgical debridement in the operating room or did not require operative intervention were not included. Patients with inadequate oral intake requiring intensive care unit follow-up and parenteral nutritional support were excluded. Patients undergoing day-case surgical procedures, those receiving corticosteroid therapy, immunosuppressed individuals, and patients with concomitant immunosuppressive conditions (such as malignancy or rheumatologic diseases) were also excluded. Patients with known chronic renal failure, end-stage renal disease, severe chronic liver disease, or hepatic failure were also excluded from the study.
Ethical approval was obtained from the University of Health Sciences Gülhane Training and Research Hospital Non-Interventional Scientific Research Ethics Committee on April 2, 2026, with decision number 2026/95.
Data Collection and Variables
Demographic characteristics (age and sex), clinical variables (length of hospital stay, duration of enteral nutrition, and duration of intravenous antibiotic therapy), and laboratory parameters including glycated hemoglobin (HbA1c), serum albumin, C-reactive protein (CRP), white blood cell (WBC) count, hemoglobin, and platelet count, were retrospectively collected from the medical records. Serum albumin levels were recorded at both admission and discharge, and changes in albumin levels during hospitalization were evaluated.
Assessment of Infection Severity
The infection component of the internationally recognized PEDIS classification categorizes diabetic foot infections into four grades based on clinical severity, ranging from Grade 1 (no clinical signs of infection) to Grade 4 (infection associated with systemic inflammatory response syndrome [SIRS]). In the present study, disease severity was assessed using this infection component. For analysis, patients were categorized into two groups based on clinical severity: PEDIS Infection Grades 1–2, representing low-to-moderate infection severity, and PEDIS Infection Grade 3, representing advanced infection severity. Clinical and laboratory parameters were compared between these groups.
Patients classified as PEDIS Infection Grade 4, characterized by SIRS or severe sepsis, were excluded because serum albumin levels in these patients are substantially influenced by systemic inflammation, capillary leakage, aggressive fluid resuscitation, and critical illness in addition to the severity of the local diabetic foot infection. To specifically evaluate the association between serum albumin levels and localized diabetic foot infection severity while minimizing the confounding effects of systemic critical illness, only patients with PEDIS Infection Grades 1–3 were included.
Statistical Analysis
Statistical analyses were performed using IBM SPSS Statistics version 27.0 for Windows (IBM Corp., Armonk, NY, USA). The distribution of continuous variables was assessed using visual methods and the Kolmogorov-Smirnov test. Normally distributed variables were expressed as mean ± standard deviation, whereas non-normally distributed variables were presented as median (minimum–maximum). Categorical variables were expressed as frequencies and percentages.
Comparisons between groups were performed using the chi-square test for categorical variables, the independent-samples Student’s t-test for normally distributed continuous variables, and the Mann-Whitney U test for non-normally distributed continuous variables. Admission and discharge serum albumin levels were compared using the Wilcoxon signed-rank test. A p-value of < 0.05 was considered statistically significant.
Univariable logistic regression analyses were first performed to evaluate factors associated with advanced infection severity, defined as PEDIS Infection Grade 3 versus PEDIS Infection Grades 1–2. Variables with a p-value < 0.05 in the univariable logistic regression analysis were subsequently entered into the multivariable logistic regression model to identify independent predictors of advanced infection severity. Results were presented as odds ratios (ORs) with 95% confidence intervals (CIs).
Results

A total of 69 patients with diabetic foot infection were included in the study. The mean age of the patients was 66.6 ± 10.6 years, and 75.4% of the cohort were male. The median length of hospital stay was 10 days (3–86), the median duration of enteral nutrition was 8 days (2–57), and the median duration of intravenous antibiotic therapy was 9 days (2–86). The median HbA1c level was 8.2% (5–16).
The median serum albumin level at admission was 3.1 g/dL (2.1–4.5), which increased to 3.3 g/dL (1.6–4.3) at discharge. The median C-reactive protein (CRP) level at admission was 129 mg/L (1–410). According to the infection component of the PEDIS classification, 20.3% of patients were classified as Grade 1, 47.8% as Grade 2, and 31.9% as Grade 3 (Table 1). These categories included 14, 33, and 22 patients, respectively.

When patients were compared according to PEDIS Infection Grade, those in the PEDIS Infection Grade 3 group, representing advanced disease severity, had significantly longer hospital stays, longer durations of enteral nutritional support, and longer durations of intravenous antibiotic therapy than those in the PEDIS Infection Grades 1–2 group (p = 0.004, p = 0.001, and p = 0.004, respectively). In addition, admission serum albumin levels were significantly lower (2.8 vs. 3.2 g/dL; p = 0.001), whereas white blood cell counts were significantly higher in the PEDIS Infection Grade 3 group (p = 0.048). CRP levels did not differ significantly between the groups, although median values were numerically higher in patients with PEDIS Infection Grade 3 (147 vs. 103 mg/L; p = 0.059). No significant differences were observed between the groups regarding HbA1c, hemoglobin, or platelet counts (Table 2).
Across the entire cohort, the median serum albumin level increased from 3.1 g/dL at admission to 3.3 g/dL at discharge, and this increase was statistically significant (p = 0.001).
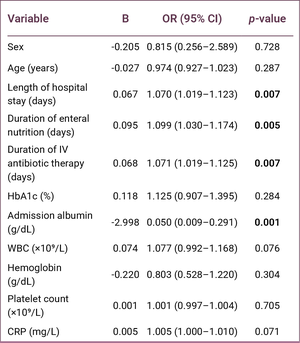
Univariable logistic regression analysis was performed to identify factors associated with advanced infection severity, defined as PEDIS Infection Grade 3 versus PEDIS Infection Grades 1–2. Length of hospital stay (OR = 1.070, 95% CI: 1.019–1.123; p = 0.007), duration of enteral nutrition (OR = 1.099, 95% CI: 1.030–1.174; p = 0.005), duration of intravenous antibiotic therapy (OR = 1.071, 95% CI: 1.019–1.125; p = 0.007), and admission serum albumin level (OR = 0.050, 95% CI: 0.009–0.291; p = 0.001) were significantly associated with advanced infection severity (Table 3). Variables with a p-value < 0.05 in the univariable analysis were included in the multivariable logistic regression model.
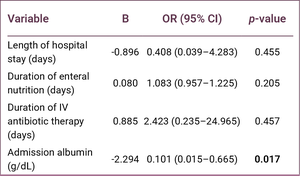
In the multivariable logistic regression analysis, only admission serum albumin remained independently associated with advanced infection severity (OR = 0.101, 95% CI: 0.015–0.665; p = 0.017). In contrast, length of hospital stay, duration of enteral nutrition, and duration of intravenous antibiotic therapy were no longer significantly associated with advanced infection severity after adjustment (Table 4).
Discussion
Diabetic foot ulcers represent a complex clinical condition that should be evaluated not only according to local wound characteristics but also in relation to infection severity, vascular status, metabolic control, tissue repair capacity, and the patient’s systemic reserve. Current guidelines recommend the assessment of diabetic foot infections based on clinical findings and the severity of infection (1,10). In the present study, disease severity was evaluated using the infection component of the PEDIS classification, and several parameters reflecting the clinical course differed significantly between patients with low-to-moderate and advanced infection severity.
In our study, the length of hospital stay, duration of enteral nutritional support, and duration of intravenous antibiotic therapy were significantly longer in the PEDIS Infection Grade 3 group than in the PEDIS Infection Grades 1–2 group. This finding suggests that advanced PEDIS stages reflect not only more severe local wounds or infections but also a greater need for intensive treatment and prolonged hospitalization. PEDIS Infection Grade 3 is associated with more complex infectious features, including deep tissue involvement, extensive cellulitis, abscess formation, gangrene, and involvement of muscle, tendon, joint, or bone structures. Therefore, prolonged antibiotic therapy, increased nutritional support requirements, and longer hospitalization in patients with advanced-stage disease are clinically expected findings (1,10). From a general surgical perspective, this observation suggests that the infection component of the PEDIS classification may serve not only as a descriptive grading system but also as a practical tool for estimating treatment intensity and healthcare resource utilization. Similarly, a previous study from our institution demonstrated that elevated HbA1c levels were associated with more advanced PEDIS infection stages and an increased need for surgical intervention. These findings support the concept that systemic biomarkers may be closely associated with disease severity in diabetic foot disease (11).
In the present study, admission serum albumin levels were significantly lower in patients with PEDIS Infection Grades. Although albumin is commonly used in clinical practice as a marker of nutritional reserve, it is also a negative acute-phase reactant whose concentration decreases in the presence of infection and inflammation (7,8). During the acute-phase response, positive acute-phase reactants such as CRP increase, whereas negative acute-phase reactants, including albumin, prealbumin, and transferrin, decrease. Consequently, low serum albumin levels in patients with infected diabetic foot ulcers may reflect not only malnutrition but also inflammatory burden, catabolic response, and reduced systemic reserve. Increased cytokine release, protein catabolism, and hepatic acute-phase responses observed in more severe diabetic foot infections may contribute to lower serum albumin levels. Therefore, low serum albumin levels may indicate not only inadequate protein intake but also the systemic inflammatory burden associated with the disease process.
For this reason, patients with PEDIS Infection Grade 4 were intentionally excluded from the present study. In these patients, serum albumin concentrations are affected by systemic inflammatory response syndrome, severe sepsis, capillary leakage, fluid resuscitation, and critical illness, making it difficult to distinguish the effects of localized diabetic foot infection from those of generalized systemic inflammation. Restricting the study population to PEDIS Infection Grades 1–3 allowed a more homogeneous evaluation of the relationship between serum albumin and infection severity. Consequently, our findings should not be extrapolated to patients with PEDIS Infection Grade 4.
The finding of lower albumin levels in the PEDIS Infection Grade 3 group supports the association between advanced disease severity and both reduced nutritional reserve and a greater systemic inflammatory response. Likewise, the higher white blood cell counts observed in the PEDIS Infection Grade 3 group further support the presence of a more pronounced systemic inflammatory response in advanced infections. CRP levels did not differ significantly between the groups, although median values were numerically higher in patients with advanced infection severity. Therefore, no conclusion was drawn based on CRP, and this finding should be interpreted cautiously in light of the relatively limited sample size. Accordingly, serum albumin should be interpreted not as a substitute for CRP or WBC, but as a complementary and readily available marker that reflects both nutritional reserve and inflammatory burden in patients with diabetic foot infection. This information may help general surgeons and wound care specialists during early clinical assessment and decision-making, particularly by identifying patients who may require closer monitoring, early nutritional assessment, and more intensive inpatient management.
Our findings partially align with those reported by Cheng et al. (12), who demonstrated an association between serum albumin levels and postoperative wound healing outcomes in patients with diabetic foot ulcers. However, unlike that study, the present study did not evaluate direct wound healing endpoints. Therefore, our results should be interpreted as supporting the association between lower serum albumin levels and greater infection severity and treatment intensity during hospitalization, rather than as evidence of impaired wound healing.
In the present study, all patients received enteral nutritional support during hospitalization, and serum albumin levels increased significantly from admission to discharge. Importantly, this does not indicate that enteral nutritional support was applied universally to all patients with diabetic foot infection as standard care; rather, the study cohort was limited to patients who were clinically identified as having inadequate oral intake and requiring enteral feeding. This selected cohort and structured nutritional support may partly explain the significant improvement in discharge albumin levels, together with surgical source control, antibiotic therapy, and resolution of the inflammatory response. This finding supports the importance of early nutritional assessment in diabetic foot patients and the provision of appropriate nutritional support in individuals with inadequate oral intake or at risk of malnutrition. Previous studies have shown that diabetes health literacy is often inadequate among diabetic foot patients and is associated with educational status, which may influence disease management, treatment adherence, and implementation of nutritional recommendations (13).
Furthermore, malnutrition has been reported to be highly prevalent among hospitalized diabetic foot ulcer patients and associated with prolonged hospitalization. In the study by Ran et al. (14), the prevalence of malnutrition was reported as 38.36%, and malnutrition was associated with an approximately threefold increase in the likelihood of prolonged hospital stay. Additionally, the current literature on nutritional support in diabetic foot ulcers emphasizes that malnutrition is a common and frequently overlooked problem in patients with chronic wounds and that protein, amino acid, and micronutrient supplementation may play important biological roles in wound healing processes (15).
Because albumin is a negative acute-phase reactant, the increase in albumin levels observed in our study should not be attributed solely to enteral nutritional support. Improvements in albumin levels may also reflect infection control, resolution of inflammation, antibiotic therapy, and overall clinical recovery following surgical treatment. Therefore, serum albumin may be considered a practical parameter for assessing nutritional and inflammatory status and monitoring the clinical course in patients with diabetic foot disease.
The main limitations of this study include its retrospective design, single-center setting, relatively small sample size, and the inability to assess nutritional status using more detailed clinical nutritional assessment tools. Although patients with known chronic renal failure, end-stage renal disease, severe chronic liver disease, or hepatic failure were excluded, overt proteinuria was not systematically evaluated as a separate variable because of the retrospective design. Therefore, unrecognized or undocumented proteinuria may have acted as a potential residual confounder affecting serum albumin levels. In addition, postoperative wound healing outcomes were not evaluated. Therefore, our findings should be interpreted as reflecting the association between serum albumin levels, infection severity, and short-term clinical course during hospitalization rather than long-term wound healing outcomes or prognosis.
Conclusion
Low serum albumin levels were associated with advanced PEDIS Infection Grades in patients with diabetic foot disease. Patients with advanced PEDIS Infection Grades had longer hospital stays, prolonged intravenous antibiotic therapy, and extended durations of enteral nutritional support. The significant increase in serum albumin levels observed during hospitalization may reflect the combined effects of nutritional support, infection control, and clinical recovery, supporting the importance of early nutritional assessment and appropriate nutritional intervention in this patient population. Serum albumin may serve as a practical biochemical parameter for evaluating infection severity and monitoring clinical progress in patients with diabetic foot disease.
REFERENCES
Schaper NC, van Netten JJ, Apelqvist J, Bus SA, Fitridge R, Game F, et al; IWGDF Editorial Board. Practical guidelines on the prevention and management of diabetes-related foot disease (IWGDF 2023 update). Diabetes Metab Res Rev. 2024;40(3):e3657. [CrossRef]
Zaman T, Canarslan Demir K, Gunduz SH, Gulap Y, Basak AM, et al. Hyperbaric oxygen therapy as an effective adjunctive treatment in the reconstruction of tissue defects with graft in diabetic foot patients: a retrospective cohort study. Int Wound J. 2025;22(6):e70686. [CrossRef]
Aydın M, Akyüz S, Yanik H, Yildirim E, Başak AM, Güven HE, et al. Autologous adipose-derived tissue stromal vascular fraction and intralesional epidermal growth factor combined application in patients with diabetic foot. J Wound Care. 2025;34(Sup3):xxx–xxxviii. [CrossRef]
Saydam M, Yılmaz KB, Bostancı MT, Turan M, Akıncı M, Yılmaz İ, et al. The use of autologous epidermal grafts for diabetic foot ulcer emergencies: a clinical study. Ulus Travma Acil Cerrahi Derg. 2022;28(3):262–7. [CrossRef]
Stechmiller JK. Understanding the role of nutrition and wound healing. Nutr Clin Pract. 2010;25(1):61–8. [CrossRef]
Can Özdemir E, Ayçiçek Tüfekçi HB, Kural E, Tekin KB, Yılmaz KB. The relationship between vitamin D levels and the presence of ulcers, balance, and mobility in patients with diabetic foot disease. Int J Low Extrem Wounds. 2026:15347346261423767. [CrossRef]
Don BR, Kaysen G. Serum albumin: relationship to inflammation and nutrition. Semin Dial. 2004;17(6):432–7. [CrossRef]
Lin Z, Zhuang W, Wang L, Lan W. Association between nutritional inflammation index and diabetic foot ulcers: a population-based study. Front Nutr. 2025;12:1532131. [CrossRef]
Vlad LG, Grosser JA, Dodenhoff KA, Peoples AE, Aguilo-Seara G, Molnar JA. Examining albumin as a bioindicator of healing capability in patients with diabetic foot ulcers: a retrospective review. Wounds. 2023;35(6):E193–6. [CrossRef]
Monteiro-Soares M, Russell D, Boyko EJ, Jeffcoate W, Mills JL, Morbach S, Game F; International Working Group on the Diabetic Foot (IWGDF). Guidelines on the classification of diabetic foot ulcers (IWGDF 2019). Diabetes Metab Res Rev. 2020;36 Suppl 1:e3273. [CrossRef]
Akyüz S, Bahçecioğlu Mutlu AB, Guven HE, Başak AM, Yilmaz KB. Elevated HbA1c level associated with disease severity and surgical extension in diabetic foot patients. Ulus Travma Acil Cerrahi Derg. 2023;29(9):1013–8. [CrossRef]
Cheng P, Dong Y, Hu Z, Huang S, Cao X, Wang P, et al. Biomarker prediction of postoperative healing of diabetic foot ulcers: a retrospective observational study of serum albumin. J Wound Ostomy Continence Nurs. 2021;48(4):339–44. [CrossRef]
Oztas B, Akyuz S, Oztas M, Güven HE, Yilmaz KB. Determination of diabetes health literacy levels of patients followed up with diabetic foot diagnosis: a cross-sectional descriptive study. Int J Low Extrem Wounds. 2025;24(4):918–25. [CrossRef]
Ran Q, Xu W, Zhao X, Sun H, Liu L, Luo Y. Risk factors for malnutrition in patients with diabetic foot ulcer and its association with prolonged length of hospitalization. Nutr Diabetes. 2024;14(1):26. [CrossRef]
Da Porto A, Miranda C, Brosolo G, Zanette G, Michelli A, Ros RD. Nutritional supplementation on wound healing in diabetic foot: What is known and what is new? World J Diabetes. 2022;13(11):940–8. [CrossRef]
Abstract
Keywords:
venous leg ulcer, lymphedema, lymphatic dysfunction, phlebolymphedema, compression therapy, bibliometric analysisIntroduction
Venous leg ulcers are among the most persistent and resource-intensive complications of chronic venous disease. They cause prolonged morbidity, repeated clinical visits, and a marked burden on patients and health systems (1,2). The usual pathophysiologic explanation focuses on venous hypertension, ambulatory venous pressure, microcirculatory inflammation, and impaired tissue repair (1). This framework is essential, but it does not fully describe the chronic edema phenotype seen in many patients. In advanced venous disease, lower-limb swelling is rarely a purely venous event. Persistent capillary filtration may exceed lymphatic transport capacity, producing lymphatic overload, secondary lymphatic damage, and the mixed venous-lymphatic state often described as phlebolymphedema (3,4).
The clinical importance of this overlap is clear. When lymphatic failure is present, edema may become more persistent, lymphorrhea more difficult to control, and tissue fibrosis more established. These changes can contribute to an increased susceptibility to cellulitis, delayed epithelialization, and recurrent ulceration (3,5,6). Compression therapy therefore does more than reduce venous hypertension; it also promotes lymphatic drainage and remains central to both venous and lymphatic care pathways (2,7,8). Despite this, many venous ulcer studies do not formally assess lymphatic dysfunction, report edema phenotype, or identify lymphedema as an outcome modifier. The condition is often recognized clinically but may be underrepresented in the literature (5,9).
This study presents a bibliometric analysis of PubMed-indexed literature on venous ulceration and lymphedema. The aim was not to perform a treatment-effect review but to clarify how often the venous-lymphatic relationship is explicitly reflected in publication titles, journals, and thematic patterns.
Materials and Methods
Data Source and Search Basis
A PubMed search was conducted on June 4, 2026, using combined search terms for venous ulcer and lymphedema. The resulting records were exported as a comma-separated values (CSV) file for analysis. The export included publication year, journal title, authorship fields, digital object identifier (DOI), PubMed Central identifier (PMCID), and title fields.
Data Processing and Statistical Analysis
The exported CSV file was analyzed in Hex.tech (Hex Technologies Inc., San Francisco, CA, USA) using Python for data cleaning, sorting, and tabulation. Descriptive statistics were used to characterize the dataset; results were reported as absolute frequencies, relative frequencies (percentages), and count distributions by year, journal, and thematic category. No inferential statistical tests were performed, as the study aimed to describe the bibliometric profile rather than to test hypotheses. Automated keyword matching was not used; thematic classification was performed by manual review of each record's title according to the predefined category list described below. The unit of analysis was the individual PubMed record.
Thematic Classification
A title-based thematic classification was applied to identify the major themes represented in the literature:
Direct venous ulcer/lymphedema overlap
Lymphedema or lymphatic terminology
Venous ulcer terminology
Compression therapy
Wound care or healing
Guideline, review, or algorithm publications
Surgical or interventional lymphatic approaches
Case reports, pilot studies, or clinical trials
Results
Overall Bibliographic Profile

The dataset contained 200 PubMed records published from 1955 to 2026 (as of June 4, 2026), distributed across 105 journals (Table 1). A DOI was available for 122 records (61.0%), while 26 records (13.0%) had a PMCID. There were 181 unique first authors, indicating a dispersed authorship structure rather than the output of a single dominant research group.
Temporal Trend
Publication activity was sparse and irregular before the 1990s and increased more substantially after 2010 (Figure 1). The largest annual totals occurred in 2016 and 2025, with 11 records in each year. Direct title-level overlap between venous ulceration and lymphedema remained consistently low, even in years with higher overall publication activity.


Although overall publication volume increased after 2010, the proportion of records using lymphedema or lymphatic terminology remained variable across decades (Figure 2). In the earliest period (1955–1989), lymphatic terms appeared in only a small fraction of the sparse output. From the 1990s onward, the use of lymphedema or lymphatic terminology became more consistent, with three of four records in 1996, three of 11 records in 2016, and four of 11 records in 2025 containing these terms. The direct venous ulcer and lymphedema overlap was limited to five individual records across the entire dataset (1955, 2007, 2023, 2024, and 2025), suggesting that the combined topic has only recently begun to appear in publication titles.
Journal Distribution


The most frequent journals were J Wound Care and Phlebologie, with 18 records each, followed by Br J Community Nurs and Br J Nurs, with nine records each (Figure 3). Nursing, vascular, dermatology, wound care, and microsurgical journals were all represented among the leading sources, reflecting the multidisciplinary nature of the topic.
Thematic Structure
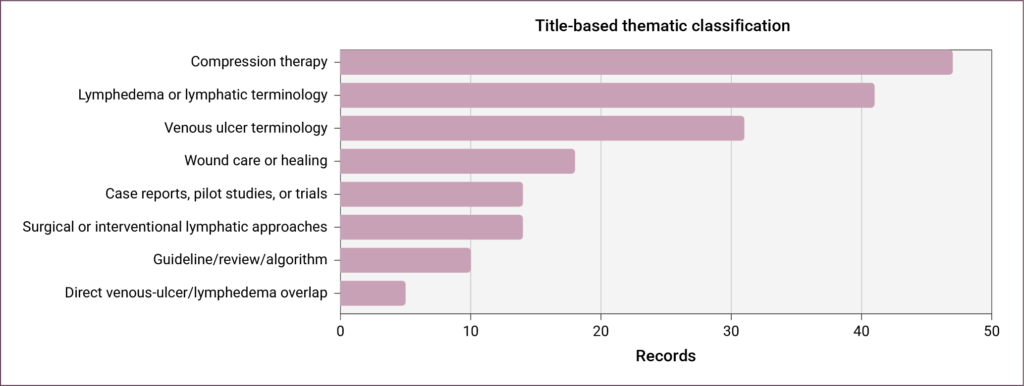
The most frequent title-based categories were compression therapy (47 records, 23.5%), lymphedema/lymphatic terminology (41 records, 20.5%), and venous ulcer terminology (31 records, 15.5%) (Figure 4). Direct venous ulcer/lymphedema overlap was identified in five records (2.5%) using the title-overlap definition. Wound care/healing terminology appeared in 18 records (9.0%), guideline/review publications in 10 records (5.0%), surgical/interventional approaches in 14 records (7.0%), and case reports, pilot studies, or clinical trials in 14 records (7.0%).


Discussion
Three practical areas dominate the literature. The first is compression therapy, which remains the shared foundation of venous and lymphatic management (2,7,8). The second is wound care, where publications address exudate, healing, dressings, and chronic ulcer management, but often without formally phenotyping lymphatic dysfunction (1,6,9). The third is a smaller interventional field focused on lymphatic surgery, including lymphovenous bypass and lymphovenous anastomosis, mainly in selected chronic or refractory cases (10–13). Importantly, treatment-pattern analyses suggest that lymphatic therapy may be undervalued for patients with phlebolymphedema and venous leg ulcer (14). This distribution may reflect daily practice: many clinicians manage both the wound and the edema, but the lymphatic component is not always separately identified, measured, or reported.

The limited explicit representation of this relationship in the literature is not merely a bibliometric detail. Lymphedema may alter prognosis, compression tolerance, infection risk, and response to standard venous ulcer care (5). Patients with persistent lymphatic failure may need more than venous correction and conventional compression. In selected cases, management may require structured edema staging, lymphatic-specific compression, manual lymphatic drainage, cellulitis prevention, skin-care protocols, lymphorrhea control, lymphatic imaging, or surgical consultation (7,8,10–15). If lymphatic status is not recorded, its influence cannot be accounted for, and clinically meaningful heterogeneity may remain unrecognized.
Future venous ulcer studies should therefore treat lymphatic dysfunction as an important clinical variable rather than an incidental observation. Baseline reporting should include edema phenotype, suspected or confirmed lymphatic insufficiency, history of cellulitis, lymphorrhea, fibrosis or skin changes, compression tolerance, and recurrence. Prospective cohorts could test whether lymphatic impairment predicts delayed healing or relapse after venous intervention. Trials of compression systems and wound care technologies should include lymphatic subgroup analyses. Finally, lymphatic imaging and microsurgical approaches require structured evaluation beyond isolated case reports.
This study has several limitations. First, the analysis was based on PubMed records only; inclusion of additional databases such as Embase, CINAHL, or Scopus might yield a larger or differently structured dataset. Second, the title-based thematic classification relied on keyword presence and did not capture themes discussed within abstracts or full texts where the venous-lymphatic relationship may have appeared without being named in the title. Third, the dataset includes records across seven decades with evolving terminology; earlier records may have used different terms for overlapping concepts, potentially underestimating the true overlap. Fourth, bibliometric metadata do not capture the depth of clinical discussion; a study may address lymphatic impairment extensively in its text without including relevant terminology in the title. Finally, the search was conducted at a single time point, and newly published or indexed records may alter the distribution.
Conclusion
Venous ulceration and lymphedema are closely connected in clinical practice, but their explicit overlap remains underrepresented in publication titles within the PubMed literature. This limited representation matters because lymphatic dysfunction may influence healing, recurrence, infection risk, and response to compression-based care. Venous ulcer research should move beyond a purely venous framework and report lymphatic status more systematically, including edema phenotype and lymphatic-specific outcomes, especially in patients with chronic edema, lymphorrhea, recurrent cellulitis, fibrosis, or refractory wounds.
REFERENCES
Burian EA, Sabah L, Karlsmark T, Kirketerp-Møller K, Moffatt CJ, Thyssen JP, et al. Cytokines and venous leg ulcer healing—a systematic review. Int J Mol Sci. 2022;23(12):6526. [CrossRef]
Sun CR, Liu MY, Ni QH, Cai F, Tang F, Yu ZY, et al. Clinical guidelines on compression therapy in venous diseases. Ann Vasc Surg. 2025;110(Pt B):183–203. [CrossRef]
Bull RH, Gane JN, Evans JE, Joseph AE, Mortimer PS. Abnormal lymph drainage in patients with chronic venous leg ulcers. J Am Acad Dermatol. 1993;28(4):585–90. [CrossRef]
Mortimer PS. Evaluation of lymphatic function: abnormal lymph drainage in venous disease. Int Angiol. 1995;14(3 Suppl 1):32–5.
Moon T, O'Donnell TF, Weycker D, Iafrati M. Impact of lymphedema in the management of venous leg ulcers. Phlebology. 2023;38(9):613–21. [CrossRef]
Aviles F Jr, Faust E. Wound care in venous disease and lymphedema. Nurs Clin North Am. 2025;60(1):77–98. [CrossRef]
Ratliff CR, Yates S, McNichol L, Gray M. Compression for lower extremity venous disease and lymphedema (CLEVDAL): update of the VLU algorithm. J Wound Ostomy Continence Nurs. 2022;49(4):331–46. [CrossRef]
Stanton J. Lymphatic insufficiency and stiff compression in venous leg ulceration. J Wound Care. 2024;33(Suppl. 1):S4–9. [CrossRef]
Gray D, Stanton J, Rouncivell D, McRobert J. Venous and lymphovenous lower limb wound outcomes in specialist UK wound and lymphoedema clinics. Br J Nurs. 2023;32(15):S12–8. [CrossRef]
Cigna E, Pierazzi DM, Sereni S, Marcasciano M, Losco L, Bolletta A. Lymphatico-venous anastomosis in chronic ulcer with venous insufficiency: a case report. Microsurgery. 2021;41(6):574–8. [CrossRef]
Mihara M, Hara H, Todokoro T, Seki Y, Iida T, Koshima I, et al. The effect of lymphatico-venous anastomosis for an intractable ulcer at the lower leg in a marked obese patient. Microsurgery. 2014;34(1):64–7. [CrossRef]
Chao S, Kuan C, Lin Y, Tai H, Cheng N. Lymphovenous bypass as an alternative strategy for managing phleboedema and venous leg ulcers: preliminary results. Plast Reconstr Surg Glob Open. 2024;12(8):e6064. [CrossRef]
Yamagiwa Y, Otani N, Oue T, Shikano Y, Nomori M, Kubo T. Lymphovenous anastomosis using pedicled deep inferior epigastric perforator flap vein for ulcer with lymphorrhea: a case report. Microsurgery. 2025;45(6):e70108. [CrossRef]
O'Donnell TF Jr, Izhakoff J, Gaebler JA, Niecko T, Iafrati MD. Correlation of disease comorbidity with prescribed treatment among insured U.S. lymphedema patients. J Vasc Surg Venous Lymphat Disord. 2021;9(2):461–70. [CrossRef]
Szolnoky G, Tuczai M, Macdonald JM, Dosa-Racz E, Barsony K, Balogh M, et al. Adjunctive role of manual lymph drainage in the healing of venous ulcers: A comparative pilot study. Lymphology. 2018;51(4):148–59.
Abstract
Keywords:
Wound, ostomy and continence nurse, occupational exposure, high-risk units, workforce policy, employment rights, specialist nursingIntroduction
Wound, Ostomy, and Continence Nurses (WOCNs) constitute an important nursing specialty that encompasses specialized care services in wound care, ostomy care, and continence care (1). The development of WOCN worldwide dates back to the late 1950s. In particular, the enterostomal therapy programs launched at the Cleveland Clinic under the leadership of Dr. Rupert Beach Turnbull and Norma N. Gill, a person with an ileostomy, marked a significant turning point in the professionalization of this field (2). Programs that initially focused solely on the rehabilitation of individuals with stomas have, over time, expanded to include wound and incontinence care. As a result, stoma care nursing has become a multidisciplinary and evidence-based field of expertise (1). Today, through international organizations such as the World Council of Enterostomal Therapists (WCET) and the Wound, Ostomy and Continence Nurses Society (WOCN), educational standards are being established in this field, specialist qualifications are being defined, and care models aimed at improving patients’ quality of life are being developed (3,4). In developed countries, WOC nurses perform their duties after obtaining a WOC specialist training certificate from an accredited body, following completion of an undergraduate or postgraduate degree (4).
WOCN development in Türkiye began in the 2000s. The first stoma therapy unit in Türkiye was established at Gazi University Hospital in 2000, marking a significant step toward the systematic provision of stoma care services (5,6). The professional identity of the field was subsequently strengthened by the establishment of the Wound, Ostomy and Incontinence Nurses’ Society (Yara Ostomi ve İnkontinans Hemşireleri Derneği [YOIHD]), the development of certified training programs, and the definition of the duties, powers, and responsibilities of the Stoma and Wound Care Nurse in the Nursing Regulations in 2011 (6,7). Founded in Türkiye in 2008, the YOIHD is a professional nursing organization dedicated to supporting and advancing the career development of nurses specializing in wound, ostomy, and incontinence care. Since 2000, the number of specialist nurses in this field has grown rapidly in Türkiye. The WOCNs in Türkiye obtain their certification by completing a 240-hour theoretical and practical training course approved by the Ministry of Health, in accordance with the Certified Training Standards for the Healthcare Sector (8). The number of Enterostomal Therapy Nursing Training Programs (ETNEP), which stood at zero in 2000, has risen to approximately 10 (9); the number of nurses certified through these programs has exceeded 650; according to YOIHD, the number of stoma therapy units has reached 36 (10), while the number of chronic wound care units reported by the Ministry of Health reached 59 as of May 2026 (11).
Nowadays, stoma and wound care units provide patients with care and rehabilitation services, as well as education and counseling, to reduce complications and improve quality of life (6). The WOCNs assume significant responsibilities within the healthcare team in their roles as caregivers, educators, consultants, researchers, and managers (5,6,12). The WOCNs work across a wide range of areas, from determining the stoma site prior to surgery to postoperative stoma and peristomal skin care, wound care, prevention of complications, and selection of appropriate care products (6,13). In addition, they play an active role in helping patients develop self-care skills (14), adapt to changes in body image (15), and improve their quality of life (13,16). By adopting evidence-based care practices, WOCNs continue to provide patient and family education, support multidisciplinary teamwork, and contribute to improving care outcomes (6,7).
In Türkiye, WOCNs carry out their duties either as an independent unit or as part of a consultation system within healthcare institutions. The WOCNs provide stoma and wound care services to patients of all ages in hospitals, not only in stoma therapy, colorectal surgery outpatient clinics, and chronic wound units, but across all departments (17,18). The WOCNs also provide care to patients in areas designated by the Ministry of Health in Türkiye as requiring special attention (19). These units include: operating rooms, angiography units, intensive care units (ICUs), palliative care centers, delivery rooms, neonatal units, pediatric wards, burn units/centers, dialysis units, emergency departments/outpatient clinics, closed psychiatric wards, alcohol and substance use treatment centers, child monitoring centers, isolation rooms, and organ, tissue, and bone marrow transplant units. The WOCNs play a role in patient care in these units and are exposed to high-risk bodily fluids such as blood, urine, feces, and exudate while providing care (20). The risk increases when nursing interventions such as wound culture collection, application of topical agents, mechanical debridement, drain management, and assistance with surgical or chemical debridement are performed.
Furthermore, WOCNs have provided care services during exceptional conditions, such as the COVID-19 pandemic, and have faced numerous physical and psychosocial risks (18,21,22). During the pandemic, WOCNs faced situations that threatened staff safety, such as the risk of exposure to COVID-19—a highly contagious infection—the risk of developing pressure injuries associated with medical devices due to the use of personal protective equipment, and being separated from their families (23,24). All these physical, biological, and psychosocial risk factors to which WOCNs are exposed clearly highlight the demanding nature of their working conditions and the high level of clinical responsibility they take on. For these reasons, appropriate regulations governing the working conditions of WOCNs are warranted.
Although WOCNs are frequently perceived as outpatient-based specialists, their clinical practice extends far beyond dedicated wound and stoma care units. In many healthcare settings, WOCNs provide bedside consultation and direct patient care in intensive care units, isolation rooms, emergency departments, palliative care centers, and other environments associated with increased occupational risk. Consequently, their actual workplace exposure may differ substantially from their formal administrative classification. Within the current healthcare system in Türkiye, WOCNs are generally classified as ‘polyclinic nurses’. As a result, WOCNs are deprived of employment benefits, such as shift allowances and the risk-related components of revolving-fund supplements provided to colleagues formally assigned to units such as ICUs, operating rooms, or emergency departments. However, WOCNs spend a significant portion of their working hours in the hospital’s high-risk and critical care units, managing complex cases directly at the patient’s bedside. As part of their duties in these settings, they work under demanding conditions that involve a high risk of infection, exposure to drug-resistant microorganisms, and the management of complex and open wounds, as well as stoma care—all of which place a heavy physical, biological, and psychological burden on them. Although studies have explored the roles, competencies, and work experiences of WOCNs (25,26), little is known about the extent of their involvement in high-risk clinical environments and whether their employment benefits reflect their actual workplace exposure. To our knowledge, no previous study has quantitatively examined the relationship between WOCNs’ time spent in high-risk units, occupational exposure, and access to employment benefits associated with high-risk clinical work. Addressing this gap is important for workforce planning, occupational health, and the recognition of specialist nursing roles. Understanding the discrepancy between WOCNs’ formal employment classification and their actual clinical exposure is essential for ensuring equitable workforce policies, occupational protection, and recognition of specialist nursing practice.
This study aimed to describe WOCNs' involvement in high-risk clinical settings, their occupational exposures, and their employment benefits in Türkiye. Specifically, the study addressed the following questions:
- What is the extent of WOCNs' involvement in high-risk clinical units?
- What occupational risks and exposures do WOCNs encounter while delivering care in these settings?
- Is there a mismatch between WOCNs' actual clinical exposure and the employment benefits they receive, and how do they perceive this situation?
Materials and Methods
Study Design and Sample
This study employed a descriptive cross-sectional design to examine WOCNs’ involvement in high-risk clinical environments, occupational exposures, employment benefits, and perceptions regarding their working conditions. Quantitative and qualitative data were collected concurrently through an online survey. The study was conducted online between April 1 and 10, 2023. The study population consisted of nurses working as WOCNs in Türkiye. No formal sampling procedure was used; the study included 100 nurses who were members of YOIHD, were working as WOCNs at the time of the study, and volunteered to participate. At the time of the study, the society had a total of 212 registered members. The study's response rate was 47.17%.
Data Collection Tools
The study used a questionnaire developed by the researchers based on the literature (17,22). The questionnaire was reviewed by researchers experienced in WOC nursing and nursing workforce research to ensure clarity, relevance, and content appropriateness prior to data collection. The questionnaire consisted of three parts and 31 questions. The first part contained nine questions on nurses’ demographic characteristics, including age, gender, educational level, years of service, and certification status. The second part consisted of 20 questions, including the amount of time WOCNs had spent working in specialist units during the previous month and the total number of patients they had cared for. The third part contained two open-ended questions: (i) What risks have you been exposed to during your work experience in units with specific characteristics as a WOCN? (ii) What are your views on your work experience in units with specific characteristics as a WOCN?
For the purposes of this study, high-risk units were defined according to the Turkish Ministry of Health regulations identifying clinical areas eligible for additional compensation due to increased occupational risk. These units include ICUs, operating rooms, emergency departments, isolation rooms, burn units, palliative care centers, dialysis units, transplantation units, and other designated specialized clinical settings.
Procedure
The data collection questionnaire was created as an online survey (Google Forms; Google LLC, Mountain View, CA, USA). The online questionnaire was sent to nurses via the WhatsApp group comprising YOIHD members. To prevent nurses from completing the survey more than once, the survey was set to ‘Limit to one response’. Data were collected by repeatedly sending messages to the group. It took approximately 5–10 minutes to complete the questionnaire.
Data Analysis
IBM SPSS Statistics, version 20.0 (IBM Corp, Armonk, NY, USA), was used to analyze the data obtained in the study. The research data were analyzed using descriptive statistics (frequencies, percentages, means, standard deviations, minimums, and maximums). The normality of continuous variables was evaluated using the Shapiro-Wilk test. Continuous variables with a normal distribution were expressed as mean and standard deviation, whereas non-normally distributed variables (e.g., time, number of polyclinic visits) were expressed as median and interquartile range (IQR).
The qualitative data obtained from the open-ended survey questions were analyzed using conventional content analysis based on the Miles and Huberman framework (27). In the content analysis, the data were examined independently by two researchers (BI, ŞG), and similar concepts were grouped together to form themes and subthemes. The themes and subthemes developed by the researchers were reviewed by the other members of the research team, and consensus was reached on the final themes and subthemes (28). The Consolidated Criteria for Reporting Qualitative Research (COREQ) guidelines were used to analyze and report the qualitative findings (29).
Ethical Considerations
Ethical approval for the study was obtained from the Gazi University Clinical Non-Interventional Research Ethics Committee on March 21, 2023, with decision no. E-77082166-604.01.02-618184. Institutional permission was obtained via e-mail from the YOIHD. In the first part of the survey questionnaire, participants were provided with preliminary information about the study and provided informed consent. The study was conducted in accordance with the Declaration of Helsinki.
Results
The study findings are presented in two sections: quantitative and qualitative results.
Quantitative Results

The mean age of the participating nurses was 37.49 ± 7.80, the mean length of service in the nursing profession was 15.94 ± 8.67 years, and the mean length of service as a WOCN was 4.67 ± 4.75 years. Among the participants, 53.0% were aged between 36–49 years, 89.0% were female, and 95.0% held a bachelor’s degree or higher. Overall, 37.0% of the nurses worked in the Central Anatolia Region, and 31.0% worked in a stoma and wound care unit. Half of the participants (50.0%) held a WOCN certificate approved by the Ministry of Health. Most participants (76.0%) did not receive the additional compensation provided to staff working in high-risk units (Table 1).
During the previous month, WOCNs spent the most time in intensive care units (median 40 [IQR, 10–80] hours), followed by isolation rooms (median 10 [IQR, 2–30] hours), and the palliative care center (median 5 [IQR, 0–38.5] hours). The units in which nurses spent the least time were the operating rooms, delivery rooms, angiography units (median 0 [IQR, 0–0] hours), dialysis units, organ, tissue and bone marrow transplantation units (median 0 [IQR, 0–0] hours), and closed psychiatric wards (median 0 [IQR, 0–0] hours) (Table 2).

During the previous month, the highest number of patients cared for by WOCNs was reported in intensive care units (median 40 [IQR, 12.75–103.55] patients), followed by emergency departments or outpatient emergency settings (median 3 [IQR, 0–39] patients), and palliative care centers (median 6.5 [IQR, 0–20] patients). The fewest patients were cared for in dialysis and transplantation units (median 0 [IQR, 0–0] patients), closed psychiatric wards (median 0 [IQR, 0–0] patients), and operating rooms, delivery rooms or angiography units (median 0 [IQR, 0–0] patients).

In their daily practice, nurses most frequently reported exposure to blood (93%), feces (89%), and urine (83%) in both stoma and wound care units and in high-risk units. The least frequently reported occupational exposures were sharps injuries (2%), radiation (2%), and scabies (1%) (Table 3).
Qualitative Results
Nurses’ views on working in high-risk clinical units were organized into two themes: disadvantages and advantages. The themes and subthemes are presented in Table 4.
Theme 1: Disadvantages
Five subthemes were identified under the theme of disadvantages: high risk of exposure to infectious diseases, lack of additional compensation, excessive workload, barriers to participation in WOCN certification programs, and assignment of certified WOCNs to duties outside their area of expertise.
Subtheme 1: High risk of exposure to infectious diseases
WOCNs who participated in the study reported facing many risks within the hospital. The WOCNs described their experiences related to this subtheme;

‘We were at high risk of infection during the pandemic and still are; since we provide care in every department of the hospital, we are exposed to many infections.’ (Participant 64, 37 years old, female).
‘With blood spurting onto my face, dealing with feces and foul-smelling, infected wound fluids, I continued to perform the care that the patient’s spouse, daughter, and mother refused to do—out of self-sacrifice, professional ethics, responsibility, and conscience—under extremely difficult conditions, adhering fully to the ethical guidelines of WOCN because I am so dedicated to this specialty...’ (Participant 94, 48 years old, female).
Another participant stated:
‘Services are provided to all units. During this process, one is exposed to the risks of all units.’ (Participant 100, 36 years old, female)
Subtheme 2: Lack of additional compensation
Participants reported that they did not receive additional compensation from hospital administration despite providing specialized services in high-risk clinical settings. Participants expressed their views as follows:
‘Although I provide services in a specialist area, I am treated as an outpatient clinic staff member when it comes to pay. The treatment we receive is unfair. Although I work 5 hours a day in high-risk ICUs, management ignores this, and assigns us to different areas. Regulations on stoma and wound care are essential.’ (Participant 99, aged 45, female)
‘As WOCNs, we are the only unit that comes into contact with patients the most, enters the same environment, and performs our duties at the patient’s bedside after our colleagues in clinical and ICUs. There must be some recognition for this effort, and additional payment should be made for this.’ (Participant 95, 33 years old, female)
‘Despite working in high-risk units, we are treated as if we were outpatient clinic nurses and receive the lowest incentive payments; we want improvements in this regard.’ (Participant 59, aged 28, female)
Subtheme 3: Excessive workload
Participants noted that WOCNs work across multiple departments in addition to hospital stoma therapy units and described the resulting workload:
‘The imbalance between the number of patients and the number of nurses is truly exhausting in terms of workload. The number of nurses should be increased to a certain extent.’ (Participant 66, 26 years old, male)
‘The work we do is very risky and exhausting; we approach the patient holistically. Our job isn’t just about providing education—it involves providing care. All patients in the hospital with wounds or stomas are under our responsibility.’ (Participant 81, 52 years old, female)
‘As a certified WOCN, I have cared for patients for long hours without distinguishing between clinical units, including those under contact isolation. Even though there are colleagues and units that handle specialized care without even touching the patient, I hope our voices are heard.’ (Participant 91, 44 years old, female)
Subtheme 4: Barriers to participation in WOCN certification programs
Some stoma and wound care nurses reported not having a WOCN certificate. One participant described her experience as follows:
‘I have been a wound care nurse for 10 years, but I don’t have a certificate. I want to enroll in the launched certificate program. As the person who set up the specialist unit, I am being, and have been, subjected to bullying. I was removed from my post...’ (Participant 98, aged 44, female).
Subtheme 5: Assignment of certified WOCNs to duties outside their area of expertise
One participant reported working in a department outside her area of expertise:
‘My new place of work is a public hospital, and I am unable to work in a department that matches my qualification.’ (Participant 71, aged 40, female)
Theme 2: Advantages
One subtheme was identified under the theme of advantages: receipt of additional compensation by WOCNs.
Subtheme 1: WOCNs receiving additional payment
One participant described her experience as follows: ‘About six months ago, I asked my supervisor for a percentage of my working hours in the intensive care units, and my request was approved; I’ve been receiving it for six months now.’ (Participant 70, 35 years old, female)
Discussion
This study demonstrated that WOCNs in Türkiye routinely provide care in high-risk clinical settings, including intensive care units, isolation rooms, emergency departments, and other specialized settings. Despite their substantial involvement in these environments and their frequent exposure to biological hazards, most participants reported not receiving the employment benefits and additional compensation provided to staff formally assigned to high-risk units.
Most nurses in the study were based in stoma and wound care units or chronic wound care units; however, they also worked in general surgery clinics, intensive care units, diabetic foot clinics, endoscopy units, and palliative care centers (Table 1). A multicenter, cross-sectional study conducted in China involving WOCNs (n = 123) reported that 77.24% of nurses worked in a stoma clinic and only 10.57% worked as full-time WOCNs. The study found that other nurses worked as WOCNs on a part-time basis while also working in the hospital in roles such as clinical nurse, manager, or instructor (25). In another study, 22.90% of WOCNs (n = 218) worked full-time (26). A cross-sectional study conducted in China (n = 247) found that 69.6% of WOCNs worked part-time in clinics, taking on duties in more than one area (30). These findings are consistent with our research results and demonstrate that WOCNs have diverse areas of practice and employment arrangements. This variation may reflect the absence of standardized national and international frameworks defining the roles, employment settings, and working conditions of WOCNs.
In Türkiye, nurses are generally required to work 40 hours per week, corresponding to approximately 160 hours per month. In our study, WOCNs spent a substantial proportion of their monthly working time in high-risk settings, including an average of 40 hours in intensive care units, 10 hours (IQR: 2–30) in isolation rooms, and 5 hours (IQR: 0–38.5) in other high-risk settings such as palliative care center (Table 2). These findings indicate that WOCNs spend a significant percentage of their working hours providing patient care in critical and high-risk environments. The qualitative findings further support this observation, as one WOCN reported: ‘…Although I work five hours a day in high-risk ICUs, management turns a blind eye to this, and we are assigned to work in different areas…’. These findings highlight the importance of aligning employment conditions and benefits with the actual clinical environments in which nurses provide care.
In hospitals, WOCNs carry out key interventions including promoting patient self-care, preventing complications, and supporting psychosocial adjustment (31). According to Turkish legislation, wound debridement, identification of the affected body area, pressure ulcer care, and burn/wound debridement are among the procedures that nurses may perform both independently and in collaboration with a doctor (1). When performing these procedures, WOCNs are exposed to physical, chemical, biological, psychosocial, and ergonomic risk factors (32). In our study, WOCNs reported exposure to both physical hazards, including blood, feces, urine, sweat, saliva, exudate, infected wound material, drain contents, COVID-19, sharps injuries, and scabies, in both stoma and wound care units and other specialized units (Table 3). Similarly, the qualitative findings identified a high risk of exposure to infectious diseases as a major disadvantage of working in these settings (Table 4). In a study evaluating wounds resulting from earthquakes, signs of infection were observed in 62.9% of wounds, and exudate was present in 65.0% (20). Similarly, a study of patients attending a wound clinic (n = 158) reported that 43.0% had a small amount of exudate, 15.8% had an infection, and 12.0% had an odor (33). These findings underscore the need to identify occupational hazards encountered by WOCNs and implement appropriate organizational and individual measures to reduce these risks.
During the COVID-19 pandemic, which affected healthcare systems worldwide, WOCNs faced a high risk of infection while providing patient care and were also assigned to duties outside their usual work units (18,22,34–36). A study conducted in Türkiye reported that 51.3% of WOCNs (n = 271) were assigned to units other than their usual workplaces during the COVID-19 pandemic (18). During this period, nurses were exposed not only to SARS-CoV-2 infection but also to the risk of medical device-related pressure injuries associated with the use of personal protective equipment (36,37). Furthermore, the postponement of surgical procedures during the pandemic led to a decline in the number of patients undergoing colorectal surgery, and WOCNs were assigned to different departments by management (36). In the present study, three WOCNs reported exposure to COVID-19 (Table 3). Assigning nurses to duties outside their areas of expertise or without consideration of their preferences may contribute to psychological stress and burnout, reduced organizational commitment, lower work productivity, and interpersonal conflict among staff (38).
Clear regulatory frameworks are important for professional development. In China, the country with the world’s second-largest population, the development of legal regulations governing WOC nursing has been recommended (12). In a study conducted with WOCNs in China, 58.30% of nurses reported that there was no performance-based system in place, and 63.80% reported that there was no promotion system for their professional positions. Similarly, 73.90% of nurses reported not receiving additional compensation, which is comparable to the 76% observed in our study (26). Nurses working in public hospitals in Türkiye receive additional payments for working in the specialist units listed in Table 2. However, despite the occupational risks associated with their work, stoma and wound care units are not classified as specialized units, and WOCNs do not receive additional payment (39). Approximately 25% of nurses in our study reported receiving additional compensation, while the rest did not (Table 1). This issue represents an important concern regarding the employment rights and working conditions of WOCNs. A study conducted in Türkiye (n = 103) reported that nurses are more likely to choose to work in areas designated as high-risk by the Ministry of Health because of the financial benefits (38). It is recommended to review the definition of high-risk units in Turkish regulations (40). Recognizing stoma and wound care units as specialized units, along with their employment conditions, could support the development of the WOC nursing workforce.
The study found that only half of the nurses held a WOCN certificate approved by the Ministry of Health. The literature indicates that ostomy care provided by clinical nurses is inadequate, that nurses lack experience in managing peristomal skin complications, and that ongoing training in this area is required (16,41,42). Care provided by certified WOCNs may improve patient satisfaction, reduce preventable complications, and enhance the quality of nursing care. The study suggests that the reasons WOCNs do not participate in certification programs include the absence of a stoma care unit in the hospital, insufficient support from hospital management, certification programs being offered in another city, and lack of financial resources.
One key issue highlighted in the study is that WOCNs were assigned to duties outside their areas of expertise. Participants reported that, in addition to their primary responsibilities in wound and stoma care, they were assigned tasks such as clinical nursing, preparing duty rosters, and performing administrative duties. In the qualitative data, this issue was reported as follows: ‘My new place of work is Public Hospital A, and I am unable to work in a department that matches my qualification.’ A descriptive study conducted with specialist nurses in Türkiye (n = 83) found that 34.9% of nurses were working in a department unrelated to their area of specialization, and that the majority of these nurses (68.97%) had not requested a transfer to a department related to their area of specialization from the hospital management (43). These findings suggest that nurses who have received specialized theoretical and practical training may nevertheless be routinely assigned to roles that do not utilize their specialist competencies. This may reflect organizational staffing requirements, limited opportunities for specialist practice, or nurses’ reluctance to challenge administrative decisions. Reports from YOIHD workshops have also emphasized the need to increase the number of certified WOCNs. According to these reports, expanding the number of certified specialists is essential for standardizing specialized care and improving patient outcomes nationwide (39,44).
This study has several limitations. Participation was limited to WOCNs who were members of a professional nursing association and volunteered to participate; therefore, the findings may not fully represent all WOCNs working in Türkiye. In addition, data regarding time spent in high-risk units, occupational exposures, and receipt of additional compensation were based on self-report and were not verified through institutional records, which may have introduced recall and reporting bias. Furthermore, WOCNs who were not members of the professional communication network used for recruitment may not have been reached.
Despite these limitations, the study has several strengths. To our knowledge, this is one of the first studies to examine WOCNs’ involvement in high-risk clinical environments, occupational exposures, and employment-related inequities. The study included participants from all seven geographical regions of Türkiye, providing a nationwide perspective on WOC nursing practice and increasing the potential transferability of the findings across healthcare settings. In addition, participants were actively working in a variety of healthcare institutions, allowing the study to capture real-world experiences from diverse clinical environments. The integration of quantitative and qualitative findings provided a comprehensive understanding of the discrepancy between WOCNs’ actual clinical responsibilities and the employment benefits they receive. The findings provide evidence that may inform workforce planning, occupational health policies, and the recognition and compensation of specialist nursing roles.
Conclusion
The findings reveal a clear mismatch between the administrative classification of WOCNs and their actual clinical responsibilities and workplace exposures. This discrepancy may contribute to employment inequities and inadequate recognition of specialist nursing practice. Workforce policies and employment regulations should be reviewed to ensure that compensation, occupational protection, and professional recognition more accurately reflect the scope and risks of WOC nursing practice.
Healthcare organizations should also support the appropriate utilization of certified WOCNs by enabling them to practice within their areas of expertise and recognizing their contributions across high-risk clinical settings. Future multicenter national and international studies are needed to examine further the relationship between specialist nursing roles, occupational exposure, workforce retention, and employment outcomes.
REFERENCES
Make an impact as a WOC nurse [Internet]. WOCN; [cited December 24, 2023]. Available from: https://cdn.ymaws.com/member.wocn.org/resource/resmgr/Updated_5.25-WOCN_Nurse_Impa.pdf
Broadwell DC. Nursing specialization: the Enterostomal Therapy nurse. Occup Health Nurs. 1983;31(1):15–9. [CrossRef]
World Council of Enterostomal Therapists. History [Internet]. WCET; [cited May 28, 2026]. Available from: https://wcetn.org/page/History
Wound, Ostomy, and Continence Nurses Society. About the WOCN Society [Internet]. Mt. Laurel (NJ): WOCN Society; [cited May 28, 2026]. Available from: https://www.wocn.org/about/
Karadağ A. Position and importance of stomatherapy units and stoma care nurse in colorectal surgery [Stomaterapi ünitelerinin ve stoma bakım hemşiresinin kolorektal cerrahideki yeri ve önemi]. Turk J Colorectal Dis. 2007;17:46–52.
Karadağ A, Kılıç H. Stoma care nursing in the world and Türkiye [Dünyada ve Türkiye’de stoma bakım hemşireliği]. In: Çavdar İ, editor. Stoma Bakım Hemşireliği. 1st ed. Ankara: Türkiye Klinikleri, 2024: 8–15.
Hemşirelik Yönetmeliği’nde değişiklik yapılmasına dair yönetmelik [Internet]. T.C. Resmi Gazete. April 19, 2011;(27910) [cited December 24, 2023]. Available from: http://www.resmigazete.gov.tr/eskiler/2011/04/20110419-5.htm
Ministry of Health. Healthcare field certified education standards: stoma and wound care nursing [Internet]. Ankara: Ministry of Health; 2015 [cited December 25, 2023]. Available from: https://dosyamerkez.saglik.gov.tr/Eklenti/46810/0/26032015-stoma-standardi-imzayapdf.pdf
T.C. Sağlık Bakanlığı Kamu Hastaneleri Genel Müdürlüğü. Stoma ve Yara Bakımı Hemşireliği Sertifikalı Eğitim Uygulama Yetkisi Alan Sağlık Tesisleri [Internet]. Ankara: Sağlık Bakanlığı; 2026 [cited May 28, 2026]. Available from: https://khgmsaglikbakimdb.saglik.gov.tr/TR-44170/1-stoma-ve-yara-bakimi-hemsireligi-sertifikali-egitim-uygulama-yetkisi-alan-saglik-tesisleri.html
Yara Ostomi İnkontinans Hemşireleri Derneği. Stomaterapi üniteleri iletişim [Internet]. YOIHD; 2026 [cited May 28, 2026]. Available from: https://www.yoihd.org.tr/files/document/stomaterapi-u-niteleri-6419e7e144c50.pdf
T.C. Sağlık Bakanlığı Sağlık Hizmetleri Genel Müdürlüğü. Chronic wound care units [Internet]. Ankara: Sağlık Bakanlığı; 2026 [cited May 28, 2026]. Available from: https://shgmshpdb.saglik.gov.tr/TR-108552/kronik-yara-bakim-uniteleri.html
Liu XL, Wang L. A review of the development and current status of wound ostomy continence nurses in the mainland of China. Int J Nurs Sci. 2018;5(2):105–9. [CrossRef]
Duluklu B, Çelik SŞ. Quality of life of persons with colostomy: problems and nursing interventions [Kolostomisi olan bireylerde yaşam kalitesi: sorunlar ve hemşirelik girişimleri]. Hacettepe Univ J Nurs Fac. 2019;6(2):111–9.
Aydogan S, Kacmaz HY, Irmak B, Aktas D, Karadag A. Effect of nursing interventions on self-care for ostomy patients: A systematic review and meta-analysis. Appl Nurs Res. 2026;89:152091. [CrossRef]
Akıl Y, Taylan S. Factors affecting adaptation of patients with intestinal stoma: a relational study [Bağırsak stomalı hastaların stomaya uyumlarını etkileyen faktörler: ilişkisel çalışma]. Cukurova Med J. 2020;45(2):428–38. [CrossRef]
Heydari A, Manzari ZS, Pouresmail Z. Nursing intervention for quality of life in patients with ostomy: A systematic review. Iran J Nurs Midwifery Res. 2023;28(4):371–83. [CrossRef]
Öztürk D, Karadağ A. Historical development process of stoma and wound care nursing: sample of Turkey. J Educ Res Nurs. 2019;16(1):73–8. [CrossRef]
Karadag A, Sengul T. Challenges faced by doctors and nurses in wound care management during the COVID-19 pandemic in Turkey and their views on telehealth. J Tissue Viability. 2021;30(4):484–8. [CrossRef]
Sağlık Bakanlığına Bağlı Sağlık Kurum ve Kuruluşlarında Görevli Personele Döner Sermaye Gelirlerinden Ek Ödeme Yapılmasına Dair Yönetmelik [Internet]. Resmi Gazete. May 12, 2006;(26166) [cited December 24, 2023]. Available from:https://khgm.saglik.gov.tr/Eklenti/23147/0/doner-sermaye-gelirlerinden-ek-odeme-yapilmasina-dair-yonetmeligipdf.pdf
Şişman H, Alptekin D, İnce S, Akıl Y. Evaluation of earthquake-related wounds; example of a university. J Tissue Viability. 2023;32(4):607–12. [CrossRef]
Maculotti D, Spena PR, Villa G. Position statement on care of ostomy patients during COVID-19 pandemic. Gastroenterol Nurs. 2020;43(4):324–6. [CrossRef]
Vural F, Özlü NGÖ. In the COVID-19 pandemic living with a stoma and being a stoma nurse. Turk J Colorectal Dis. 2020;30(4):231–7. [CrossRef]
Aksoy M, Büyükbayram Z. The prevalence, characteristics, and related factors of pressure injury in medical staff wearing personal protective equipment against COVID-19 in Turkey: a multicenter cross-sectional study. J Tissue Viability. 2022;31(2):207–12. [CrossRef]
Uçar Ö, Çelik S, Altun E, Karahan E. The prevalence of facial pressure injuries among nurses during COVID-19 pandemic and its relationship to COVID-19 infection. J Tissue Viability. 2022;31(4):699–706. [CrossRef]
Yu S, Yao X, Sang Y, Lin Y, Huang Y, Che X, et al. Status of core competencies of wound, ostomy and continence nurses and their influence on career success: a cross-sectional study. BMJ Open. 2022;12(11):e063239. [CrossRef]
Zhang M, Ei D, Zhu X, Chen Y. Training and management status of wound, ostomy, and continence nurses: a cross-sectional survey from China. Cureus. 2022;14(4):e23793. [CrossRef]
Baltacı A. Miles-Huberman Model in qualitative data analysis [Nitel veri analizinde Miles-Huberman modeli]. AEÜSBED. 2017;3(1):1–14.
Hsieh HF, Shannon S. Three approaches to qualitative content analysis. Qual Health Res. 2005;15(9):1277–88. [CrossRef]
Tong A, Sainsbury P, Craig J. Consolidated criteria for reporting qualitative research (COREQ): a 32-item checklist for interviews and focus groups. Int J Qual Health Care. 2007;19(6):349–57. [CrossRef]
Shi L, Yue L, Liu X, Gong X, Li B. Interprofessional collaboration and associated factors among wound, ostomy, and continence nurses: a cross-sectional study in China. PeerJ. 2025;13:e20006. [CrossRef]
Panattoni N, Mariani R, Spano A, Leo A, Iacorossi L, Petrone F, et al. Nurse specialist and ostomy patient: competence and skills in the care pathway. A scoping review. J Clin Nurs. 2023;32(17–18):5959–73. [CrossRef]
Gürer A. Employee safety in health services. J Health Serv Educ. 2018;2(1):9–14.
Erkin A, Yılmaz AÇ, Açıl HC, Yaman Ö, Gül A, Aygin D. Evaluation of wound follow-up results of patients applying to the wound outpatient clinic. J İzmir Fac Med. 2022;1(3):142–9. [CrossRef]
Ateş T, Önal B, Kaptan D, Kurt Y, Öztürk H. Nursing care of a patient COVID-19 diagnosis according to international classification for nursing practice system: a case report. J Curr Nurs Res. 2021;1(1):32–43.
Özkaya BÖ, Atar B. Nursing care of a patient with colostomy in the COVID-19 pandemic. J Health Life Sci. 2021;3(1):111–4.
Pontieri-Lewis V. Adapting WOC nursing practice to the COVID-19 pandemic: a view from here. J Wound Ostomy Continence Nurs. 2020;47(4):321–3. [CrossRef]
Çakar V, Karadağ A, Bugan B, Kılıç H, Demir AS. Personal protective equipment-related problems experienced by healthcare workers, solutions, and recommendations: a qualitative study. Adv Skin Wound Care. 2023;36(11):1–9. [CrossRef]
Yeşiltaş A, Gül İ. Nurses’ working units and why they prefer to work of that units. MAKU J Health Sci Inst. 2016;4(2):74–87.
Yara Ostomi İnkontinans Hemşireleri Derneği. XIII. Ulusal I. Marmara Bölgesi Stoma ve Yara Bakım Hemşireleri Toplantı Raporu [Internet]. YOIHD; May 2024 [cited May 28, 2026]. Available from: https://www.yoihd.org.tr/tr/yayinlar/calistay-raporlari-4
Kıroğlu F. Working conditions and general problems in the COVID-19 pandemic environment. Meyad Akademi. 2020;1(1):79–90.
Alenezi A, Kimpton A, McGrath I, Livesay K. Confidence, skills and barriers to ostomy patient care by nursing staff in Saudi Arabia. Nurs Forum. 2022;57(3):403–11. [CrossRef]
Li F, Deng B, Xu L, Song M, Li X. Practice and training needs of staff nurses caring for patients with intestinal ostomies in primary and secondary hospitals in China: a cross-sectional survey. J Wound Ostomy Continence Nurs. 2019;46(5):408–12. [CrossRef]
Ateş N, Harmancı Seren AK, Tuna R. An evaluation of the compatibility of specialist nurses’ units and their areas of expertise. J Health Nurs Manag. 2024;11(3):424–33. [CrossRef]
Yara Ostomi İnkontinans Hemşireleri Derneği. XII. Stoma ve Yara Bakım Hemşireleri Toplantısı Genel Raporu [Internet]. YOIHD; September 15, 2021 [cited July 18, 2026]. Available from: https://www.yoihd.org.tr/files/publication/2021-sybh-toplantisi-genel-raporu-632abcada09f3.pdf